
SlideServe
Menu
Préférences
© SlideServe · v2026

Clinical case

hallie avatar
4 diapositives · 576 Views · Sep 20, 2014

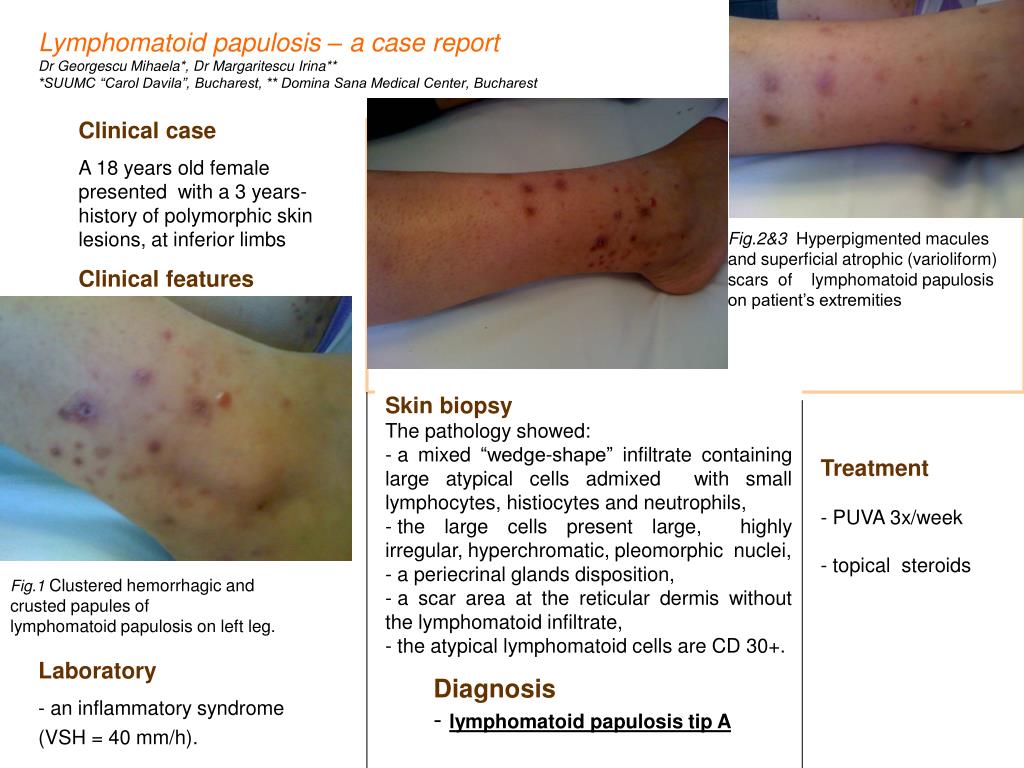
Lymphomatoid papulosis – a case report Dr Georgescu Mihaela*, Dr Margaritescu Irina** *SUUMC “Carol Davila”, Bucharest, ** Domina Sana Medical Center, Bucharest. Clinical case A 18 years old female presented with a 3 years-history of polymorphic skin lesions, at inferior limbs
Clinical case - slide 1
01 / 4Clinical case
1 / 17

Télécharger la présentation

Clinical case
Une image / un lien ci-dessous est fourni (tel quel) pour télécharger la présentation

Politique de téléchargement : le contenu du site vous est fourni TEL QUEL pour votre information et votre usage personnel ; il ne peut être vendu, concédé sous licence ni partagé sur d’autres sites sans l’accord de son auteur.Le contenu vous est fourni TEL QUEL, pour votre information et votre usage personnel uniquement. Téléchargez la présentation en cliquant sur ce lien. Lors du téléchargement, si vous ne parvenez pas à télécharger une présentation, l’éditeur a peut-être supprimé le fichier de son serveur.Pendant le téléchargement, si vous ne parvenez pas à obtenir une présentation, le fichier a peut-être été supprimé par l’éditeur.

F I N

Plus de contenu associé

Transcription de la présentation
  1. Lymphomatoid papulosis – a case report Dr Georgescu Mihaela*, Dr Margaritescu Irina** *SUUMC “Carol Davila”, Bucharest, ** Domina Sana Medical Center, Bucharest Clinical case A 18 years old female presented with a 3 years-history of polymorphic skin lesions, at inferior limbs Clinical features Fig.2&3Hyperpigmented macules and superficial atrophic (varioliform)scars of lymphomatoid papulosis on patient’s extremities • Skin biopsy • The pathology showed: • a mixed “wedge-shape” infiltrate containing large atypical cells admixed  with small lymphocytes, histiocytes and neutrophils, • the large cells present large, highly irregular, hyperchromatic, pleomorphic nuclei, • a periecrinal glands disposition, • a scar area at the reticular dermis without the lymphomatoid infiltrate, • the atypical lymphomatoid cells are CD 30+. Treatment - PUVA 3x/week - topical steroids Fig.1Clustered hemorrhagic and crusted papules of lymphomatoid papulosis on left leg. Laboratory - an inflammatory syndrome (VSH = 40 mm/h). Diagnosis - lymphomatoid papulosis tip A

  2. Histopathology Lymphomatoid papulosis – a case report Dr Georgescu Mihaela*, Dr Margaritescu Irina** *SUUMC “Carol Davila”, Bucharest, ** Domina Sana Medical Center, Bucharest Fig.4 HEx50 Figure 5. HEx200 Figure 6. HEx400 Figure 4,5 Fragment of cutaneous biopsy withmixed “wedge-shape” infiltrate containing large atypical cells admixed  with small lymphocytes, histiocytes and neutrophils Figure 6. Lymphomatoid papulosis type A lesion with predominance of large atypicallymphoid cells, displaying polymorphic nuclei, prominent nucleoli, and abundant cytoplasm Figure 7,8 Numerous CD 30+ cells are present. Figure 7. HEx200 Figure 8. HEx400

  3. Lymphomatoid papulosis – a case report Dr Georgescu Mihaela*, Dr Margaritescu Irina** *SUUMC “Carol Davila”, Bucharest, ** Domina Sana Medical Center, Bucharest Introduction Lymphomatoid papulosis is a peculiar condition, caractherized by a chronic, recurrent, self-healing papulonecrotic or papulonodular eruption with histopathological features suggestive of a (CD 30 – positive) malignant lymphoma The pathogenesis • unknown • a possible viral-driven etiology • a low-grade lymphoma induced by chronic antigenic stimulation • studies show a high rate of apoptosis contributing to regression, mediated by death-receptor pathway signaling via cell surface Fas (CD95) signaling and/or due to increased levels of the proapoptotic protein bax. Mutations of TGF-β signaling receptor genes results in disease progression Differential diagnosis • viral infections (herpes virus, molluscum contagiosum, parapox virus (milker's nodule), Epstein-Barr virus, HTLV1, HIV ) • scabies • syphilis • superficial fungal infections • pityriais lichenoides et varioliformis acuta • atopic dermatitis • drug reactions (particularly to anticonvulsants) • mycosis fungoides or a lymphomatoid drug reaction (type B lymphomatoid papulosis) • Treatment • - active treatment -not necessary(few non-scarring lesions) • - no treatment has proven consistently effective • - beneficial effects from: • PUVA • topical mechlorethamine or carmustine • low-dose etoposide • Clinical features • typicalskin lesions are red-brown papules and nodules that may develop central hemorrhage, necrosis and crusting, which disappear within 3-8 weeks • characteristically, lesions are often at different stages • of development

  4. Lymphomatoid papulosis – a case report Dr Georgescu Mihaela*, Dr Margaritescu Irina** *SUUMC “Carol Davila”, Bucharest, ** Domina Sana Medical Center, Bucharest Histological types Differential diagnosis Type A - Scattered CD30+, large Hodgkin lymphoma Type B - Epidermotropic CD30-/+ small Mycosis fungoides Type C - Cohesive sheets CD30+, large ALCL Type D - Epidermotropic CD30+ CD8+ small AECTCL (Berti lymphoma) Type E - Angioinvasive CD30+ CD8+>CD4+Extranodal NK/T, GD-TCL References 1. McKee’s Pathology of the Skin, Chapter 29 – Cutaneous lymphoproliferative diseases and related disorders, John Goodlad,Eduardo Calonje, Lymphomatoid papulosis, 4th edition, Elsevier, 2012 2. Skin Lymphoma: The Illustrated Guide, Lorenzo Cerroni et al, CD30+ lymphoproliferative disorders. Lymphomatoid papulosis3rd Edition, Wiley, 2009 3. Dermatology, By By Jean L. Bolognia et al., Chapter 120. Primary cutaneous CD30-positive lymphoproliferative disorder. Lymphomatoid papulosis, 3rd Edition, Elsevier, 2012 4. Self assessmentCourse in Virtual Dermatopathology, Dr. Werner Kempf, Case 02, EADV Congress, Istanbul, 2-6 oct 2013 Conclusions • The disease is now classified as an indolent lymphoma in the new WHO classification • The clinicopathological and immunohistochemical correlation is essential in establishing the diagnosis  The evolution of the disease is characterized by recurrence